Dental Crowns for Misshapen Teeth: A Cosmetic and Functional Fix

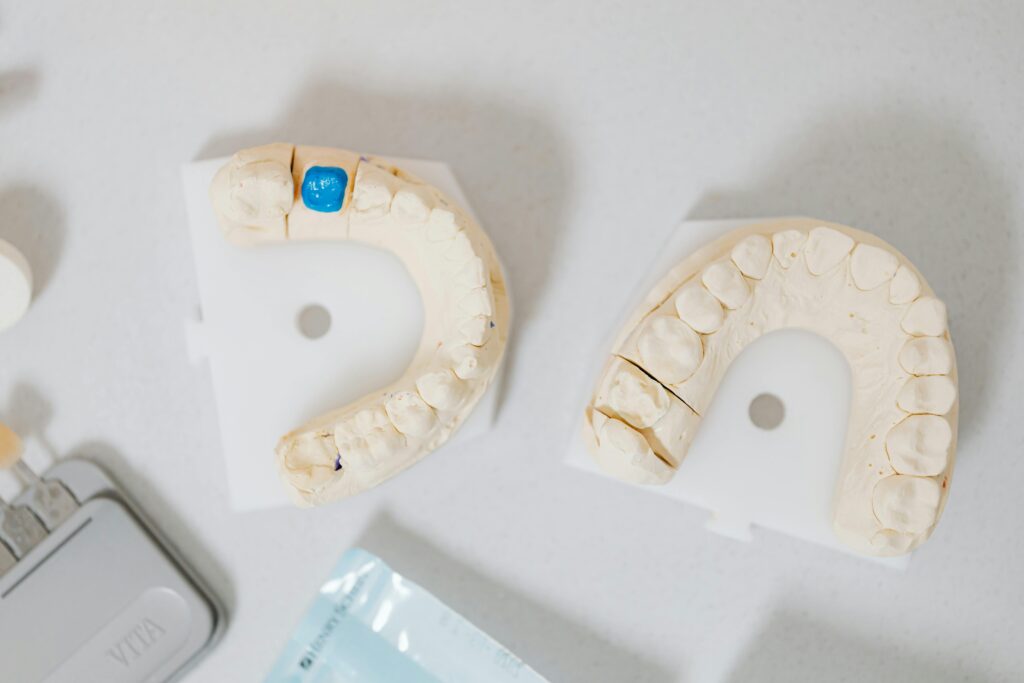
A misshapen tooth rarely stays a purely cosmetic issue for long. Patients usually notice the appearance first, a tooth that looks too small, too pointed, too worn, twisted, or oddly proportioned compared with the rest of the smile. After that, the practical complaints begin to surface. Food catches in places it should not. The bite feels uneven. A front tooth chips again and again. Speech may even change slightly when the shape of an incisor is far outside the norm.
This is where Dental Crowns often enter the conversation. A crown can change the size, contour, and strength of a tooth in a way that few other restorations can. It is one of the most versatile tools in cosmetic and restorative dentistry, but it is not a casual fix. Done well, a crown can make a misshapen tooth disappear into the smile and function comfortably for years. Done poorly, it can feel bulky, look flat, irritate the gums, or create a bite problem that did not exist before.
The right question is not simply whether a crown can cover a misshapen tooth. It usually can. The better question is whether a crown is the most conservative and durable option for that specific tooth, in that specific mouth, for that specific patient.
What counts as a misshapen tooth
Misshapen teeth come in more varieties than most people realize. Some are developmental, meaning the tooth emerged that way. Peg laterals are a common example, where the upper lateral incisors are noticeably smaller and narrower than usual. Some teeth are malformed because enamel did not develop normally. Others became misshapen over time through grinding, erosion, fractures, old fillings, or trauma.
In practice, the shape problem often falls into one of a few patterns. The tooth may be too small relative to neighboring teeth. It may have an irregular edge, deep grooves, or a conical appearance. It may be heavily worn down and look squared off or shortened. In other cases, it has enough natural tooth structure, but the contour causes the bite to hit in the wrong place.
Not every shape issue needs the same treatment. A tiny lateral incisor in a 22-year-old with otherwise healthy teeth raises a different set of decisions than a 58-year-old molar that is worn, cracked, and out of proportion after years of clenching. From the chairside perspective, shape is only half the story. The other half is strength.
Why crowns can work so well in these cases
A Dental Crown covers the visible part of the tooth and allows the dentist to redesign it in three dimensions. That matters because shape is not only about what the tooth looks like from the front. It is also about the side profile, the contact point with adjacent teeth, the way the tooth meets the opposing arch, and the contour where the crown meets the gumline.
Bonding can alter some of those features. Veneers can alter others. But crowns give the greatest control when a tooth needs a substantial change in form and added protection at the same time.
That combination is especially valuable in situations where the original tooth is both unattractive and structurally compromised. Think of a tooth with a developmental defect and a large old filling. Or a front tooth that is naturally undersized and has chipped repeatedly. Or a premolar that angles oddly in the bite and has become increasingly worn. In those cases, a crown is not just a cosmetic shell. It becomes a way to restore proper anatomy and improve function.
A well-designed crown can do several jobs at once. It can make the tooth appear wider or longer. It can close a dark triangle or a minor space. It can rebuild a worn chewing surface. It can improve the contact with adjacent teeth so food does not pack in. It can help distribute bite forces more evenly. For many patients, that is the appeal, one treatment, several problems addressed.
When a crown is the right choice, and when it is not
The decision becomes clearer when you compare what is being asked of the restoration. If the tooth only needs a modest cosmetic enhancement and has strong, intact enamel, a crown may be more treatment than necessary. Composite bonding or a porcelain veneer might preserve more natural tooth structure. That matters, especially for younger patients.
A crown becomes more compelling when the tooth already has significant damage, a Dental Crowns large filling, a crack, severe wear, or a shape that cannot be corrected predictably with a more conservative option. In those situations, the dentist is not removing a pristine tooth merely for appearance. The tooth already needs reinforcement.
Here is a practical way I explain it to patients: if the issue is mostly on the surface, think bonding or veneers first. If the issue involves the whole architecture of the tooth, a crown deserves serious consideration.
That said, there are edge cases. A peg lateral may be corrected beautifully with bonding in one person and better with a crown in another. A badly worn canine might seem like a crown case until you discover the patient grinds aggressively and has untreated bite instability, which means any restoration is at risk unless the underlying forces are managed. Dentistry rarely rewards one-size-fits-all thinking.
Common scenarios where crowns make sense
A few patterns come up repeatedly in clinical practice:
- a tooth that is misshapen and also heavily restored
- a worn tooth that has lost height and now affects the bite
- a front tooth with repeated chipping because the original shape is too thin or weak
- a malformed tooth with enamel defects that compromise appearance and durability
- a misshapen tooth that cannot be corrected predictably with bonding alone
Those are not the only situations, but they are among the most common. In each one, the crown is doing more than masking an imperfection. It is rebuilding the tooth.
Cosmetic gains are real, but proportion matters more than perfection
Patients often arrive with a mirror image in mind. They want the odd tooth to match the others exactly. Sometimes that is possible. More often, the better goal is harmony rather than duplication.
Natural smiles are not machine-made. Incisors differ slightly in length. Canines carry a subtle point. Premolars transition shape between the front and back of the mouth. A crown that is too symmetrical or too idealized can stand out more than the original problem.
The strongest cosmetic outcomes come from careful attention to proportion. Width-to-length ratio matters. So does translucency at the edge, surface texture, and how the crown reflects light compared with neighboring teeth. A front tooth that is technically the right color can still look wrong if it is too opaque or too smooth. I have seen crowns replaced for shade when the real issue was contour.
This is especially important for a single front tooth. Matching one central or lateral incisor is among the most demanding tasks in dentistry because the human eye notices asymmetry immediately. In that setting, the dentist and laboratory need excellent communication, good photography, and sometimes a trial phase to confirm the shape before the final ceramic is made.
Functional benefits patients do not always expect
Appearance usually gets people through the door. Comfort often becomes the thing they appreciate most afterward.
A properly contoured crown can improve how floss passes between teeth, how the tongue moves around the tooth, and how the bite settles during chewing. It can reduce the constant awareness some patients feel when a tooth has an odd shape. Small improvements in contour can also reduce food trapping, which is a frequent complaint with malformed premolars and molars.
There is also a protective benefit. Teeth that are unusually shaped are sometimes prone to stress concentration in thin areas. Rebuilding those contours with a crown can lower the risk of recurrent fractures, provided the bite is adjusted correctly and habits like clenching are addressed.
That last point deserves emphasis. A crown does not make a tooth indestructible. It makes the tooth more serviceable. If a patient has heavy grinding, edge-to-edge biting, or nail-biting habits, the design of the crown must account for those realities, and a night guard may be part of the long-term plan.
Material choices shape the result
Not all crowns are the same, and material selection influences both beauty and longevity. For misshapen front teeth, all-ceramic options are often preferred because they mimic enamel more convincingly. They can show depth, translucency, and subtle color variation that metal-based restorations may not capture as naturally.
For back teeth, the conversation can shift toward strength, space, and bite forces. Zirconia has become a common choice because it is durable and can perform well in high-load areas. Porcelain-fused-to-metal crowns still have a place in some situations, though they are used less often than before for highly aesthetic zones.
The key is not choosing the most expensive material by default. It is matching the material to the tooth’s location, the patient’s bite, the cosmetic demand, and how much room exists for the restoration. A beautifully translucent ceramic can fail if placed in a setting where it is too thin and under too much force. Likewise, a very strong opaque material may solve a fracture risk while creating an aesthetic compromise that bothers the patient every time they smile.
The preparation question patients worry about most
Many people hesitate when Dental Crowns they hear that a tooth must be prepared for a crown. That concern is reasonable. Crowns do require reshaping the tooth to create space for the material and a path of insertion. This is one reason a crown should not be the reflex answer to every cosmetic problem.
How much preparation is needed depends on the starting shape of the tooth, the planned material, and the amount of correction required. A severely protruding or malformed tooth may actually need a meaningful reduction to achieve a natural contour. A smaller tooth may need less aggressive preparation in some areas and more in others, especially if the goal is to build out width or length without creating bulk.
The preparation should be deliberate, not generic. Overprepared teeth can become sensitive or lose unnecessary structure. Underprepared teeth often lead to crowns that are overcontoured and harder to clean. The best crown work usually looks easy from the outside because the planning behind it was exacting.
What the process usually looks like
The appointment sequence varies somewhat by office and technology, but most crown cases for misshapen teeth involve careful records first. This may include photographs, digital scans, bite analysis, and discussion of shape preferences. For visible teeth, some dentists create a wax-up or mock-up so the patient can preview the proposed contours.
At the preparation visit, the tooth is reshaped, an impression or scan is made, and a temporary crown is placed in most cases. Temporary restorations are more important than patients realize. They let the dentist test length, contour, phonetics, and bite before the final crown is made. If a patient says, “This feels too long,” or “My S sounds are different,” that information is useful and should not be brushed aside.
The final appointment is not just a quick cementation. Fit, contacts, margin integrity, color, and bite all need to be checked. Minor adjustments can make the difference between a crown that disappears into the dentition and one that feels foreign for months.
Temporary crowns reveal a lot
Some of the best decisions in crown dentistry happen during the temporary phase. A patient may discover that the idealized longer tooth they wanted in photographs taps first when they chew. Or they may realize that the broader shape they were unsure about actually balances their smile beautifully.
I remember a case involving a small, malformed upper lateral incisor on a patient in her early thirties. She came in wanting the tooth “bigger but not obvious.” The mock-up looked a little conservative on the model, almost too subtle. In the mouth, it was exactly right. Any wider and it would have crowded the canine visually and made the smile less natural. That kind of judgment is hard to achieve by measurements alone. Live try-ins matter.
Potential downsides and trade-offs
Crowns solve many problems well, but they are not free of downside. Tooth reduction is the main one. Once a tooth has been prepared for a crown, it will always need a crown or another full-coverage solution in the future.
There is also the possibility of sensitivity, gum irritation, chipping of ceramic, or recurrent decay at the margin if oral hygiene slips. A crown that looks beautiful on day one can become a problem if it traps plaque because the contour is too full or the margin extends into a hard-to-clean area.
Cost is another practical factor. Crowns are more expensive than bonding and often more involved than veneers, depending on the case. Insurance may cover part of the fee if there is a restorative need, but purely cosmetic upgrades are less consistently covered. The financial aspect should be discussed plainly before treatment starts.
Then there is the issue of expectations. A crown can dramatically improve a single tooth, but it may also make neighboring teeth look more worn or discolored by comparison. Sometimes one well-done crown becomes the first step in a broader smile plan, even if that was not the original intention.
Crowns versus bonding and veneers
This is the comparison patients ask for most often, and the honest answer is that each option has a distinct lane.
Bonding is conservative and often cost-effective. It can be excellent for small shape corrections, especially in younger patients or as a reversible first step. Its limitations are durability, stain resistance, and the difficulty of managing larger contour changes under significant bite pressure.
Veneers are ideal when the front surface of the tooth needs aesthetic enhancement and the underlying structure is healthy. They preserve more tooth than crowns in many cases. However, veneers do not wrap and reinforce the tooth the way crowns do, so they are less suitable when the tooth is already compromised or when major reshaping is needed around the entire circumference.
Crowns provide the broadest correction and the greatest structural coverage. That power is exactly why they should be used selectively. The goal is not to choose the most comprehensive treatment. The goal is to choose the least invasive treatment that can predictably do the job.
Longevity depends on more than the crown itself
Patients naturally want a number. How long will it last? A fair answer is that many crowns serve well for a decade or longer, and some last much longer than that. But lifespan depends heavily on the bite, the material, hygiene, gum health, and whether the patient clenches or grinds.
I have seen elegant ceramic crowns fail early in mouths with heavy parafunctional forces and no night guard. I have also seen older crowns remain stable for many years because the margins were excellent and the patient kept meticulous home care. The restoration matters, but the environment matters just as much.
The teeth next to the crown also play a role. If contacts shift, if gum recession exposes margins, or if decay starts under the edge of the crown, the restoration may need replacement even if the ceramic itself is intact.
Aftercare is simple, but consistency matters
Once the crown is in place, maintenance is straightforward and not very glamorous. The patients who do best are the ones who keep the basics boring and regular.
- brush thoroughly at the gumline twice daily
- floss carefully around the crown and adjacent teeth every day
- wear a night guard if grinding or clenching is part of the picture
- avoid using the teeth as tools for opening packages or biting hard objects
- return for regular exams so small margin or bite issues are caught early
Most crown problems do not begin as dramatic failures. They begin as small issues, a rough spot, a slightly open margin, a contact that traps food, a patient who stops wearing their guard. Catching those changes early usually keeps the solution simpler.
Choosing the right dentist for a shape correction case
Not every crown dentist approaches misshapen teeth with the same eye. Technical competence is essential, but so is aesthetic judgment. The dentist should be comfortable discussing tooth proportions, smile line, surface texture, and bite, not just the mechanics of placing a cap over the tooth.
Before-and-after photos are useful if they reflect cases similar to yours. So is a willingness to slow down and preview the shape, especially for front teeth. In cosmetic-functional cases, the planning phase often predicts the result more accurately than the brand of scanner or milling unit.
Ask how the final shape will be tested before permanent cementation. Ask whether a temporary or mock-up will be used. Ask what material is being recommended and why. Clear answers usually signal thoughtful treatment planning.
The bottom line for patients weighing a crown
For the right tooth, a crown can be transformative. It can correct an awkward shape, protect weakened structure, improve the bite, and restore confidence in a smile that has felt uneven for years. It is one of the few treatments that can genuinely handle cosmetic and functional demands at the same time.
It is also a treatment that asks for respect. A crown is not just a prettier outer layer. It is a full-coverage restoration that changes the future of that tooth. When the indication is sound and the execution is precise, Dental Crowns can be an excellent answer for misshapen teeth. When they are used out of convenience or without careful planning, they can create the very problems patients hoped to escape.
The smartest path is usually the most tailored one. Look at the tooth, the bite, the age of the patient, the amount of existing damage, and the cosmetic goal. If a crown is truly the best fit, it can deliver a result that feels natural in the mouth and looks unremarkable in the best possible way, as though the tooth had always belonged there.
Omni Dental Specialty
1690 E Gonzales Rd, Oxnard, CA 93036, United States
+1 805-410-9603
FAQ About Dental Crowns
How long do crowns last on teeth?
A dental crown often lasts about five to fifteen years, although some last longer. Material, the underlying tooth, oral hygiene and grinding habits affect longevity. Regular dental examinations help identify wear, decay or a loose crown; no lifespan is guaranteed.
How much does a tooth crown cost?
There is no single price for every crown. Material, laboratory work, the condition of the tooth and any additional treatment affect the fee. Ask for a written estimate and confirm your insurance benefits, exclusions and out-of-pocket costs before treatment.
What is the downside of crowns on teeth?
A conventional crown usually requires irreversible removal of some tooth structure. Possible problems include sensitivity, chipping, loosening and decay at the crown margin; some teeth later need root canal treatment. Discuss your tooth's condition, material choices and suitable alternatives with your dentist.